Trichotillomania (TTM) is a primary psychiatric disorder with dermatological signs that can manifest as patchy hair loss anywhere on the body, including the pubic region. The disorder causes clinically significant distress or impairment in social, occupational, or other important areas of functioning.
Any hair surface can be affected; however, the most common areas are the scalp, eyebrows and eyelashes, with the anterior scalp and vertex being particularly involved. The lower eyelid lashes are usually not involved, which helps differentiate TTM from alopecia areata. The areas of hair loss are often found on the side of the body contralateral to the dominant hand. Alopecia plaques tend to have an artificial appearance, are generally circular, and contain hairs of various lengths and shapes. Signs of inflammation are not usually present in TTM, though intense scratching can produce excoriation, lichenification, erythema and postinflammatory hyperpigmentation in some cases.
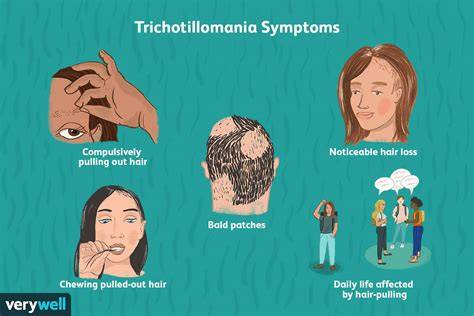
Most people with TTM pull their hair in private and try to hide the disorder. They may be consciously aware of pulling and develop elaborate rituals for doing so, or they may pull unconsciously. Some individuals alternate between conscious and unconscious pulling depending on mood and situation. Occasionally, patients exhibit other repetitive behaviors such as skin picking, nail biting, or cheek biting.
TTM must be differentiated from other causes of patchy non-scarring hair loss. Alopecia areata is a major diagnostic consideration but presents as oval, well-demarcated plaques with a relatively soft skin surface, and a hair-polyp test around alopecia areata areas yields telogenic hairs. In TTM, there are signs of recently broken and plucked hairs and surrounding hairs may appear artificial. Nails may help differentiate; nails in alopecia areata may show nail pitting, while nails in TTM are typically normal.
Tinea (fungal infection) is another common misdiagnosis; a KOH exam and Woods lamp can help rule out non-inflammatory tinea. When considering scalp involvement, trichotillomania in the scalp must be distinguished from androgenetic alopecia (bilateral, diffuse thinning) or telogen effluvium (diffuse shedding). Well-defined unilateral alopecia plaques are more characteristic of TTM.
Management of TTM is influenced by age of onset. In preschool-aged children, where pulling might resemble thumb-sucking behavior, the most effective approach is parental education and support, recognizing that spontaneous resolution often occurs with maturation. In infants, loving care, maternal skin contact, and transitional objects can be beneficial. For older children and teenagers, accurate diagnosis is essential and reassurances that hair growth will occur if pulling stops are often sufficient. Referral to mental health professionals should be considered when appropriate.
No medication has been approved specifically for TTM. Pharmacotherapy has largely been disappointing in efficacy. Prognosis depends largely on age at onset: the prognosis is excellent in young children and generally good in late childhood and adolescence.
In clinical practice, a comprehensive approach includes psychoeducation, behavioral strategies, and, when needed, referral for mental health evaluation. Cognitive-behavioral therapy and habit reversal training have shown utility, while pharmacological options have not demonstrated consistent, robust benefit in randomized trials.
Other common body-hair loss considerations include conditions such as alopecia areata, telogen effluvium, and androgenetic alopecia, as well as hair loss due to hormonal changes, nutritional deficiencies, or inflammatory or infectious processes. Alopecia areata typically presents with oval plaques; telogen effluvium presents as diffuse shedding; and androgenetic alopecia tends to be bilateral and patterned.
Pubic hair loss can arise from excessive hair removal, hormonal changes, frontal fibrosing alopecia, atrophic vaginitis, chemotherapy, radiation therapy, infections such as sexually transmitted infections, iron deficiency anemia, or systemic inflammatory or autoimmune conditions. In severe cases, pubic hair loss may cause psychological distress, though it is not typically dangerous to physical health. Treating underlying causes-such as hormonal imbalance, nutritional deficiencies, infections, or initiating cancer therapy-can help regrowth, though some treatments may be temporary or contingent on ongoing disease activity.
In aging individuals or those experiencing hormonal shifts, pubic hair thinning can be a normal part of aging or a sign of endocrine changes. PCOS can cause excess pubic and other body hair in women, often treated with hormonal therapies when appropriate. Where hair loss is due to treatment such as chemotherapy or radiation, regrowth may occur after completion, though some cases experience permanent loss depending on radiation dose and location.
When pubic hair loss is noted, seeking a medical evaluation is advisable to determine whether hair regrowth can be supported through lifestyle adjustments, nutrition, and targeted therapies. A doctor may assess iron levels, thyroid function, and other metabolic factors, and discuss potential referrals for dermatology or mental health services if trichotillomania or other behavioral concerns are suspected.
Overall, pubic hair loss has a spectrum of etiologies from benign to serious. Early identification of the underlying cause improves the chances for regrowth and reduces psychological distress.
Key distinguishing signs and diagnostic pointers
- TTM shows recently broken and irregularly shed hairs with surrounding hairs appearing artificial.
- Alopecia areata tends to have oval plaques with relatively soft skin and may exhibit nail pitting in some cases.
- Tinea is ruled out with KOH and Woods lamp examination.
- Unilateral, well-defined plaques point toward TTM rather than diffuse patterns seen in telogen effluvium or androgenetic alopecia.
Treatment and management considerations
Management hinges on age of onset and underlying factors. In preschoolers, parent-focused education and supportive strategies are central, with the expectation of spontaneous resolution. For broader populations, a combination of behavioral therapies, psychoeducation, and, where appropriate, treatment of comorbid psychiatric conditions is recommended. No medication has proven universally effective for TTM, and prognosis remains favorable in younger patients with appropriate interventions.

For pubic hair loss due to other causes, management may include addressing hormonal imbalances, nutritional deficiencies, infections, or chemotherapy/radiation-related effects. General hair-preserving practices, such as avoiding aggressive hair removal, gentle washing, and conditioning, can support existing hair during regrowth attempts.
How I Manage My ✨TRICHOTILLOMANIA✨ (compulsive hair-pulling)
If you experience significant hair loss and psychological distress, consult a healthcare provider for a thorough evaluation and a personalized treatment plan. Early discussion with a clinician can help identify the underlying cause and guide appropriate interventions.