Pityriasis rubra pilaris (PRP) is a rare skin disorder that causes inflammation of the skin, thickening of the nails and at times shedding of the hair. The classic adult type, the most prevalent subcategory, had previously been reported to resolve within three years. The largest case series to date, however, demonstrated that courses are often much longer than this. The peak onset years of PRP are in the first, sixth and seventh decades of life. While it most commonly affects adults, there is a significant proportion of pediatric patients affected. There are five types of PRP, which are classified based on age of onset and body areas affected. The sixth type of PRP, or HIV associated, has been more recently described but is still debated.
PRP is an ultra-rare skin disorder. In fact, it is considered an orphan disease. PRP patients and their caregivers quickly learn that every case of PRP is unique. Unfortunately, there is no specific or consistently effective therapy for PRP. In fact, there are no treatments approved by the US Food and Drug Administration (FDA) or the European Medicines Agency (EMA) for use in PRP. Nevertheless, experts tend to use a multimodal approach including topical and systemic therapies to control the symptoms of the disorder.
Topical therapies can reduce skin inflammation and aid with itch and dryness. The diagnosis of PRP can best be made using several well-described clinical features of the most common form, type 1 or classic adult. Patients describe rough, perifollicular, erythematous papules that coalesce to form large, scaly plaques. The palms and soles are frequently involved with an orange-red, waxy keratoderma. Nails may become thickened, discolored, ridged, cluttered with debris under the free-edge and may even shed. Hair may shed considerably due to the disorder itself or some treatments used.
In March 2003, English dermatologist Dr. Andrew Griffiths reinforced that fact when he titled his Dowling Oration to the British Association of Dermatologists “Pityriasis Rubra Pilaris - The Scarlet Pimpernel”. The disease has a long historical description, with several figures in dermatology contributing to its recognition as a distinct entity. The International Center for Toxicology and Medicine notes that a differential diagnosis is a method by which a physician determines what disease process has caused a patient’s symptoms. A biopsy is often important in making the diagnosis of PRP, though histology is not pathognomonic and many features are non-specific.
Clinical Variants and Features
There are five variants of PRP: classic adult (type I), atypical adult (type II), classic juvenile (type III), circumscribed juvenile (type IV), and atypical juvenile (type V). A sixth variant for HIV-associated PRP has been proposed. Type I PRP is the most common and may begin with perifollicular hyperkeratosis and erythematous bases, often on the hands, wrists, and trunk, with plaques that can coalesce into erythroderma. Type II shows ichthyosiform lesions, eczematous scaling, and a coarser keratoderma. Type III resembles Type I but may clear within 3 years of onset. Type IV is focal and common in prepubertal children, with sharply demarcated areas of erythema and follicular hyperkeratosis on elbows, knees, and bony prominences. Type V resembles Type II or shows lamellated keratoderma of the palms and soles with ichthyosiform scaling, typically presenting in early life with a more chronic course. Type VI, the proposed HIV-associated type, presents with nodulocystic or pustular acneiform lesions and often resembles lichen spinulosus or hidradenitis suppurativa.
In classic adult PRP, signs include pink to red patches that may progress to erythroderma, with palmoplantar keratoderma and fissures that can be painful. Scalp involvement with diffuse scale and erythema is common, and nail changes such as thickening and discoloration are frequent. Alopecia can occur, and mucous membranes are rarely involved. The disease can affect eyes, with potential ectropion in prolonged facial erythroderma. PRP can be associated with systemic symptoms such as malaise, fever, or chills, especially in acute onset, and electrolyte disturbances may occur with widespread erythroderma.
The PRP journey often includes remission and relapse cycles. While 90% of PRP patients may achieve full remission within 1-5 years, this timetable is not guaranteed, and atypical forms may require long-term coping strategies. The presence of pruritus, pain, and sleep disturbance is common, and support groups can be helpful during the acute phase. Recovery is viewed by the PRP community as a restoration of health or function, with milestones such as the return of sweat, leaving the house for essentials, or improved skin texture celebrated along the way.
The etiology of PRP remains largely unknown. A combination of genetic predisposition, environmental triggers, and other unknown factors is believed to contribute. CARD14 mutations have been identified in both familial and sporadic cases, implicating NF-κB signaling in pathogenesis. Some suggest immune dysregulation and antigenic triggers, including infections or UV exposure, as possible initiators of the inflammatory cascade that drives PRP lesions.
Diagnosis and Differential Diagnosis
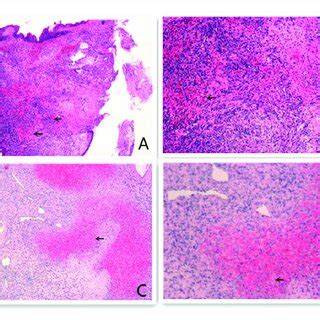
Clinical observation forms the initial basis for diagnosis, with signs such as dry, red, and flaky skin, and palmoplantar keratoderma guiding assessment. Biopsy is used to rule out other skin diseases; histology may reveal hypergranulosis, follicular plugging, acanthosis, and other nonspecific changes. Direct immunofluorescence is typically unhelpful as immunoglobulins and complement are usually negative. The differential diagnosis includes psoriasis and eczema, which can be distinguished by histopathology, clinical pattern, and distribution, though exceptions exist.
PRP has been described in association with dermatomyositis (the Wong variant) and with various malignancies as a paraneoplastic phenomenon, though these associations are uncommon. Paraneoplastic PRP may resolve with treatment of the underlying cancer in some cases. Familial PRP is rare and often autosomal dominant, with onset in early life and a more chronic course.
Treatment and Management
There is no definitive, universally effective treatment for PRP, and no FDA or EMA approved therapies specifically for PRP. Management is typically multimodal and tailored to disease type, extent, and patient factors. First-line systemic therapies often include retinoids, with acitretin preferred by many clinicians due to favorable efficacy and dosing considerations, though isotretinoin, etretinate, and alitretinoin have also been used. In acute flares or extensive disease, systemic corticosteroids may provide rapid control, but long-term reliance is avoided due to side effects. Methotrexate is another common systemic option, with the caveat of potential myelosuppression and hepatotoxicity, particularly when combined with retinoids.
Topical therapies include emollients and barrier creams for dryness, keratolytics (such as salicylic acid) to reduce scaling, and topical corticosteroids to decrease inflammation. For palmoplantar keratoderma, potent topical steroids may be employed. Biologics have shown activity in refractory PRP cases, including TNF inhibitors (infliximab, adalimumab, etanercept), IL-12/23 inhibitors (ustekinumab), and IL-17/IL-23 inhibitors (secukinumab, ixekizumab, guselkumab, risankizumab), with various response patterns reported in case series and single-center studies. A phosphodiesterase-4 inhibitor, apremilast, has also been used in refractory cases with some success. Topical imiquimod has been explored in limited contexts, though practicality is restricted by body surface area involvement.
For juvenile forms, less toxic regimens are recommended due to higher spontaneous resolution rates in children. Patient education about the natural history of PRP is essential, with emphasis on potential spontaneous improvement within several years and the generally non-life-threatening nature of the disease. Support groups and patient education materials can provide necessary psychosocial support during the course of PRP.
Emerging research at Thomas Jefferson University aims to build a PRP patient registry and to study CARD14 mutations, contributing to understanding genetic underpinnings and guiding future therapies. Controlled clinical trials remain limited due to the rarity of PRP, resulting in reliance on case reports and series to guide treatment decisions.
Prognosis and Living with PRP
Remission is defined as the disappearance of signs and symptoms, whether medication-induced or natural. Recovery emphasizes restoration of health or function and is celebrated as milestones. The disease follows a waxing and waning pattern, with episodes of exacerbation and remission. In many patients, remission occurs within a few years, but timelines vary widely by type and individual factors. Regular monitoring is important, particularly for patients with erythroderma, to detect electrolyte disturbances, infections, and hypoalbuminemia. HIV-associated PRP and paraneoplastic forms may have more complex courses and require integrated care.
Overall, PRP remains a complex, poorly understood condition with a heterogeneous clinical spectrum. The medical community emphasizes individualized, multimodal treatment strategies, patient education, and ongoing research to improve outcomes for those affected.
An Introduction to PRP